|
Case Report
A case of SPG11-associated hereditary spastic paraparesis identified by the “ear of the lynx sign”
1 Sr. Consultant Neurologist & Academic Coordinator, Institute of Neurosciences, Indraprastha Apollo Hospitals, New Delhi 110076, India
2 DrNB Neurology, Indraprastha Apollo Hospitals, New Delhi 110076, India
3 Attending Consultant Neurology, Institute of Neurosciences, Indraprastha Apollo, Hospitals, New Delhi 110076, India
4 Attending Consultant Neurology, Indraprastha Apollo Hospital, New Delhi 110076, India
5 Clinical Fellow (Neurology), Indraprastha Apollo Hospital, New Delhi 110076, India
Address correspondence to:
Pushpendra Nath Renjen
C-85, Anand Niketan, New Delhi 110021,
India
Message to Corresponding Author
Article ID: 100022N06PR2025
Access full text article on other devices

Access PDF of article on other devices

How to cite this article
Renjen PN, Priyaranjan M, Chaudhari DM, Goswami A, Saeed N. A case of SPG11-associated hereditary spastic paraparesis identified by the “ear of the lynx sign”. Edorium J Neurol 2025;10(2):1–6.ABSTRACT
Hereditary spastic paraparesis (HSP) is a genetically and clinically heterogeneous group of disorders with the common feature of progressively worsening spasticity of the lower extremities, often with variable degrees of weakness. Spastic paraplegia type 11 (SPG11) mutations are the most frequent form of autosomal recessive hereditary spastic paraplegia (ARHSP) which represents the complicated form of HSP. Additional features may include cognitive dysfunction, extrapyramidal dysfunction, cerebellar dysfunction or peripheral neuropathy among other features. Imaging findings include a thin corpus callosum although this is not unique to SPG11-related HSP. A characteristic abnormality in these patients affecting the region of the forceps minor of the corpus callosum has been described as the “ears of the lynx” sign. We present a case of a man in his 20s who presented with gradually progressive lower limb spasticity along with weakness, with a history of non-progressive childhood onset action tremors of the right hand. Magnetic resonance imaging (MRI) findings revealed a thin corpus callosum with “ears of the lynx” sign thereby raising the possibility of ARHSP. Electrodiagnostic studies revealed electromyography evidence of both lower motor neuron (LMN) and upper motor neuron (UMN) changes in bulbar and multiple spinal segments with modest fasciculations, scanty fibrillations, and severe spastic recruitment. Whole exome sequencing revealed a compound heterozygous variant in the SPG11 gene thereby confirming the diagnosis of SPG11-related HSP. This case outlines the importance of “ears of the lynx” sign in diagnosis of SPG11-related HSP and simultaneous presence of additional LMN features in SPG11-related HSP, thereby creating a diagnostic overlap with familial amyotrophic lateral sclerosis.
Keywords: HSP, SPG11, ARHSP
INTRODUCTION
Hereditary spastic paraparesis (HSP) is a genetically and clinically heterogeneous group of disorders with the common feature of progressively worsening spasticity of the lower extremities, often with variable degrees of weakness. It is a rare neurodegenerative disorder and the characteristic pathology is retrograde degeneration of the longest nerve fibers in the corticospinal tracts and posterior columns due to mutations affecting vesicular trafficking, axonal transport, lipid metabolism, mitochondrial dynamics, and myelination. It may be inherited in an autosomal dominant, autosomal recessive, or X-linked fashion, although a number of cases will lack a family history [1],[2]. Although most cases present in the second to fourth decades, onset is from infancy into the eighth decade. The clinical syndrome is broadly divisible into the pure form and the complicated form. In the pure form, patients develop only lower-extremity spasticity with weakness, but some of these cases eventually become complicated. Complicated form includes optic neuropathy, pigmentary retinopathy, deafness, ataxia, ichthyosis, amyotrophy, peripheral neuropathy, dementia, autoimmune hemolytic anemia/thrombocytopenia (Evans syndrome), extrapyramidal dysfunction, cerebellar dysfunction, ptosis, ophthalmoparesis, intellectual disability and bladder dysfunction.
Spastic paraplegia type 11 (SPG11) mutations are the most frequent form of autosomal recessive hereditary spastic paraplegia (ARHSP) which manifests with complicated features as mentioned earlier. It maps to chromosome 15q21, and has 100,982 coding nucleotides which are translated into a protein with 2443 amino acid, SPATACSIN. This protein is particularly expressed in the neurons of the cerebellum and cerebral cortex [3]. The mutations can lead to absence or functional impairment of SPATACSIN protein. Spastic paraplegia type 11 is seen along with Parkinsonism and upper body neuron spastic phenotypes [4]. Pathologically, the mutations of SPG11 primarily cause progressive degeneration of the upper motor neurons (UMNs), but lower-limb muscle atrophy and fasciculations are also observed in patients carrying SPG11 mutation, indicating the involvement of lower motor neuron (LMN). Furthermore, LMN alterations can be found on electromyography (EMG) [5],[6],[7]. A characteristic manifestation of SPG11 is the presence of a thin corpus callosum (TCC) in the MRI scanning [8], and SPG11 gene mutations account for 41–77% of ARHSP-TCC cases [3],[5],[9],[10]. The treatment of HSPs remains symptomatic and should be tailored to the individual symptoms, such as use of baclofen to alleviate spasticity. Patients may benefit from a multidisciplinary approach that includes physiotherapy, speech therapy, and occupational therapy. We report a case of autosomal recessive hereditary spastic paraparesis associated with SPG11 mutation.
CASE REPORT
A man in his 20s born from a non-consanguineous marriage presented with an insidious onset and gradually progressive symmetrical lower limb spasticity and weakness of five years duration leading to difficulty in walking, without any symptoms suggestive of a cranial nerve deficit, upper limb weakness or spasticity, bulbar weakness and muscular atrophy. He also had non-progressive low amplitude mild tremulousness of the right hand with predominant complaint of difficulty in writing over last 13 years. Neurological examination revealed normal mental status with no evidence of any cranial nerve involvement. The patient had a scissoring gait with severe clasp knife spasticity of both lower limbs. Motor power in both lower limbs and both upper limbs was 3/5 and 5/5, respectively. Bilateral knee and ankle jerks were exaggerated with sustained patellar and ankle clonus and bilateral extensor plantars. Muscle wasting and fasciculations were absent and sensory examination was within normal limits. Action tremor of right upper limb was seen without any cerebellar signs. The patient had six siblings and family history was positive with similar disease in one of his brothers and two of his sisters, with disease onset between the ages of 20 and 25 years in all affected siblings.
Investigations
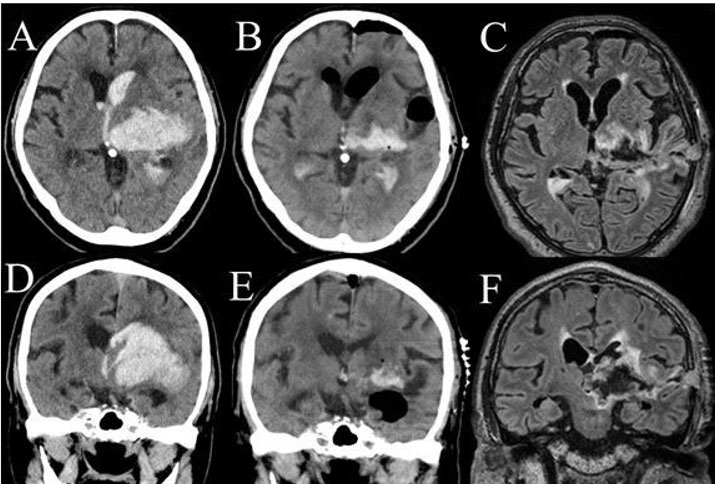
Routine biochemical and hematological workup did not reveal any abnormality. Cerebrospinal fluid (CSF) examination revealed mildly raised protein (61.2 mg/dL) with normal glucose and no cells. Electrodiagnostic studies revealed normal nerve conduction velocities (NCVs) with EMG evidence of both LMN and UMN changes in bulbar and multiple spinal segments with modest fasciculations, scanty fibrillations, and severe spastic recruitment characterized by synchronous recruitment of large number of motor units. Based on the energy dispersive X-ray (EDX) findings along with the clinical scenario, a diagnosis of complicated HSP as well as familial amyotrophic lateral sclerosis (ALS) was considered. Brain MRI revealed dysgenesis of the corpus callosum with severe atrophy of the rostrum, genu, and anterior body of the corpus callosum and partial atrophy of the posterior body and splenium with white matter hyperintensity in the periventricular region predominantly in the frontal regions giving rise to the classical “ear of the lynx sign” (Figure 1). Magnetic resonance imaging screening of the whole spine revealed no spinal cord abnormalities. In view of the clinical findings of spastic paraparesis along with a strong family history and the classical MRI findings, the patient was evaluated for a genetic cause. Whole exome sequencing test reported a compound heterozygous variant in the SPG11 gene associated with Spastic paraplegia 11 with one variant present in Exon 21: c.3623C>T (p.Pro1208Leu) and the other was at Exon 34: c.6347C>G (p.Thr2116Arg) thus confirming the diagnosis of SPG11-related hereditary spastic paraparesis.
Differential diagnosis
Initial differential diagnosis considered was familial ALS. Clinical features were consistent with UMN findings and EMG revealed the presence of fasciculations. Imaging findings revealed thin corpus callosum and the typical “ear of the lynx” sign suggestive of SPG11-related HSP. Finally, whole exome sequencing report of the compound heterozygous variant in the SPG11 gene along with UMN symptoms and imaging findings of thin corpus callosum with the “ear of the lynx” sign, made it clear that we were dealing with HSP related to SPG11 mutation.
Outcome and follow-up
The patient had modest clinical improvement in spasticity with the use of oral baclofen with a resultant improvement in gait. Motor weakness of lower limbs was stable with neither improvement nor any deterioration. He was subsequently discharged on oral baclofen with advice to follow up on outpatient basis.

DISCUSSION
Diagnosis of SPG11-HSP is based on the presence of slowly progressive spastic paraparesis, MRI findings of thin corpus callosum and identification of pathogenic mutations in the SPG11 gene. Magnetic resonance imaging shows a thin corpus callosum, but this sign is not unique to HSP-TCC, and there are patients with HSP-TCC caused by SPG11 mutations, where corpus callosum has normal thickness. Thinning of the corpus callosum could be primary or secondary and generalized or focal. Failed or abnormal myelination can cause primary thinning, usually related to hypomyelination leukoencephalopathies, metabolic disorders affecting white matter, and microcephaly. Diffuse injury can cause secondary thinning mainly due to factors such as hypoxic-ischemic encephalopathy, human immunodeficiency virus (HIV) encephalopathy, hydrocephalus, dysmyelinating, and demyelinating conditions. Focal disturbance of formation or focal injury also causes localized thinning, e.g., callosal dysgenesis, metabolic disorders with localized effects, hypoglycemia, white matter injury of prematurity, HIV-related atrophy, infarction, vasculitis, trauma, and toxins [11]. A thin corpus callosum may also occur in other subforms of HSP, including SPG15 (spastizin, 14q22), SPG21 (maspardin, 15q22), SPG32 (14q12), SPG47 (AP4B1, 1p13), and HSP-TCC with epilepsy (8p12) and occasionally in SPG4 (SPAST, 2p22) and SPG7 (paraplegin, 16q24).
A characteristic abnormality in these patients affecting the region of the forceps minor of the corpus callosum has been described as the “ears of the lynx” sign [12]. The forceps minor of the corpus callosum, corresponding to the genu fibers, has prolonged T1 and T2 values. As a result, this region appears bright on T2-weighted and dark on T1-weighted images. On axial sections, the abnormality bears a remarkable resemblance to the ears of a lynx, with the areas of abnormal signal reminiscent of the tufts of hair crowning the tips of the ears of this animal. The presence of this MRI finding in a seemingly sporadic case could be useful to guide genetic testing and help in separating patients with genetic mutations from those who may show a similar radiologic finding caused by more common etiologies, such as gliosis at the calloso-caudate angle of the frontal horn of the lateral ventricles or multiple sclerosis. The ears of the lynx MRI sign suggests the presence of a genetic mutation, likely characteristic of SPG11 or SPG15, in patients with cognitive impairment or a spastic paraparesis.
Our patient presented with slowly progressive spastic paraparesis with MR findings of callosal atrophy leading to thinning of the corpus callosum and the “ear of the lynx” sign. Whole exom sequencing revealed a SPG11 mutation which led to the confirmation of diagnosis. Features of complicated HSP in our patient included EMG evidence of fasciculations and fibrillations in bulbar and multiple spinal segments along with the presence of action tremors.
Progressive degeneration of the upper motor neurons (UMNs) is seen primarily due to mutations of SPG11. Additionally, lower-limb muscle atrophy and fasciculations are also observed in such patients who carry SPG11 mutation which eventually indicates involvement of lower motor neurons (LMN). Furthermore, LMN alterations can be found in electromyography (EMG) [5],[6],[7]. Furthermore, like in our case, these patients can rarely present with tremors (seen in 1 out of 37 gene-proven cases) [5]. The involvement of SPG11 in UMNs and LMN degeneration is further underlined by the finding that pathogenic mutations of SPG11 have also been identified in patients with autosomal-recessive juvenile amyotrophic lateral sclerosis (ARJALS) [13]. SPG11 mutations were recently reported to be associated with ARJALS with unusually long disease durations in 2 independent studies [12],[13]. Although a clinical overlap can be considered, there is an apparent clinical heterogeneity between the ARHSP and ARJALS. First, these patients’ phenotype differs from the typical phenotype of ALS. This is due to the presence of TCC shown by the brain MRI in all patients, as well as the occurrence of cognitive deficits or mental health problems in some of the pedigrees. Second, although both LMN and UMN clinical signs can be present, the UMN signs predominate. However, while the clinical presentation of SPG11 can be complex and overlaps with cerebellar ataxia, leukodystrophies, and other disorders, certain features are usually not present in pure or complicated HSPs. They should make the clinician suspicious of an alternative diagnosis. This includes profound involvement of the upper extremity or bulbar muscles or diurnal fluctuations and dopa responsiveness (as seen in dopa-responsive dystonia).
CONCLUSION
Ear of the lynx sign when present becomes an important imaging feature for diagnosis of SPG11-related HSP in the right clinical context.
Complicated HSP associated with SPG11 mutations can have a wide range of clinical presentation with simultaneous UMN and LMN features thereby creating a diagnostic confusion specially with familial ALS.
Predominance of upper motor neuron features favors complicated HSP over familial ALS.
REFERENCES
1.
Depienne C, Tallaksen C, Lephay JY, Bricka B, Poea-Guyon S, Fontaine B, et al. Spastin mutations are frequent in sporadic spastic paraparesis and their spectrum is different from that observed in familial cases. J Med Genet 2006;43(3):259–65. [CrossRef]
[Pubmed]

2.
Lan MY, Yeh TH, Chang YY, Kuo HC, Sun HS, Lai SC, et al. Clinical and genetic analysis of Taiwanese patients with hereditary spastic paraplegia type 5. Eur J Neurol 2015;22(1):211–4. [CrossRef]
[Pubmed]
3.
Paisan-Ruiz C, Dogu O, Yilmaz A, Houlden H, Singleton A. SPG11 mutations are common in familial cases of complicated hereditary spastic paraplegia. Neurology 2008;70(16 Pt 2):1384–9. [CrossRef]
[Pubmed]
4.
Pozner T, Regensburger M, Engelhorn T, Winkler J, Winner B. Janus-faced spatacsin (SPG11): Involvement in neurodevelopment and multisystem neurodegeneration. Brain 2020;143(8):2369–79. [CrossRef]
[Pubmed]
5.
Stevanin G, Azzedine H, Denora P, Boukhris A, Tazir M, Lossos A, et al. Mutations in SPG11 are frequent in autosomal recessive spastic paraplegia with thin corpus callosum, cognitive decline and lower motor neuron degeneration. Brain 2008;131(Pt 3):772–84. [CrossRef]
[Pubmed]
6.
Winner B, Gross C, Uyanik G, Schulte-Mattler W, Lürding R, Marienhagen J, et al. Thin corpus callosum and amyotrophy in spastic paraplegia—Case report and review of literature. Clin Neurol Neurosurg 2006;108(7):692–8. [CrossRef]
[Pubmed]
7.
Iskender C, Kartal E, Akcimen F, Kocoglu C, Ozoguz A, Kotan D, et al. Turkish families with juvenile motor neuron disease broaden the phenotypic spectrum of SPG11. Neurol Genet 2015;1(3):e25. [CrossRef]
[Pubmed]
8.
Castro-Fernández C, Arias M, Blanco-Arias P, Santomé-Collazo L, Amigo J, Carracedo Á, et al. Targeted NGS meets expert clinical characterization: Efficient diagnosis of spastic paraplegia type 11. Appl Transl Genom 2015;5:33–6. [CrossRef]
[Pubmed]
9.
McDermott C, White K, Bushby K, Shaw P. Hereditary spastic paraparesis: A review of new developments. J Neurol Neurosurg Psychiatry 2000;69(2):150–60. [CrossRef]
[Pubmed]
10.
Stevanin G, Santorelli FM, Azzedine H, Coutinho P, Chomilier J, Denora PS, et al. Mutations in SPG11, encoding spatacsin, are a major cause of spastic paraplegia with thin corpus callosum. Nat Genet 2007;39(3):366–72. [CrossRef]
[Pubmed]
11.
Andronikou S, Pillay T, Gabuza L, Mahomed N, Naidoo J, Hlabangana LT, et al. Corpus callosum thickness in children: An MR pattern-recognition approach on the midsagittal image. Pediatr Radiol 2015;45(2):258–72. [CrossRef]
[Pubmed]
12.
Riverol M, Samaranch L, Pascual B, Pastor P, Irigoyen J, Pastor MA, et al. Forceps minor region signal abnormality “ears of the lynx”: An early MRI finding in spastic paraparesis with thin corpus callosum and mutations in the spatacsin gene (SPG11) on chromosome 15. J Neuroimaging 2009;19(1):52–60. [CrossRef]
[Pubmed]
13.
Orlacchio A, Babalini C, Borreca A, Patrono C, Massa R, Basaran S, et al. SPATACSIN mutations cause autosomal recessive juvenile amyotrophic lateral sclerosis. Brain 2010;133(Pt 2):591–8. [CrossRef]
[Pubmed]
SUPPORTING INFORMATION
Author Contributions
Pushpendra Nath Renjen - Conception of the work, Design of the work, Acquisition of data, Analysis of data, Drafting the work, Revising the work critically for important intellectual content, Final approval of the version to be published, Agree to be accountable for all aspects of the work in ensuring that questions related to the accuracy or integrity of any part of the work are appropriately investigated and resolved.
Mayank Priyaranjan - Conception of the work, Design of the work, Acquisition of data, Analysis of data, Drafting the work, Revising the work critically for important intellectual content, Final approval of the version to be published, Agree to be accountable for all aspects of the work in ensuring that questions related to the accuracy or integrity of any part of the work are appropriately investigated and resolved.
Dinesh Mohan Chaudhari - Conception of the work, Design of the work, Acquisition of data, Analysis of data, Drafting the work, Revising the work critically for important intellectual content, Final approval of the version to be published, Agree to be accountable for all aspects of the work in ensuring that questions related to the accuracy or integrity of any part of the work are appropriately investigated and resolved.
Avinash Goswami - Conception of the work, Design of the work, Acquisition of data, Analysis of data, Drafting the work, Revising the work critically for important intellectual content, Final approval of the version to be published, Agree to be accountable for all aspects of the work in ensuring that questions related to the accuracy or integrity of any part of the work are appropriately investigated and resolved.
Nayaab Saeed - Conception of the work, Design of the work, Acquisition of data, Analysis of data, Drafting the work, Revising the work critically for important intellectual content, Final approval of the version to be published, Agree to be accountable for all aspects of the work in ensuring that questions related to the accuracy or integrity of any part of the work are appropriately investigated and resolved.
Guaranter of SubmissionThe corresponding author is the guarantor of submission.
Source of SupportNone
Consent StatementWritten informed consent was obtained from the patient for publication of this article.
Data AvailabilityAll relevant data are within the paper and its Supporting Information files.
Conflict of InterestAuthors declare no conflict of interest.
Copyright© 2025 Pushpendra Nath Renjen et al. This article is distributed under the terms of Creative Commons Attribution License which permits unrestricted use, distribution and reproduction in any medium provided the original author(s) and original publisher are properly credited. Please see the copyright policy on the journal website for more information.